The Checkup, Explained: A Step-by-Step Walkthrough of Your Annual Physical
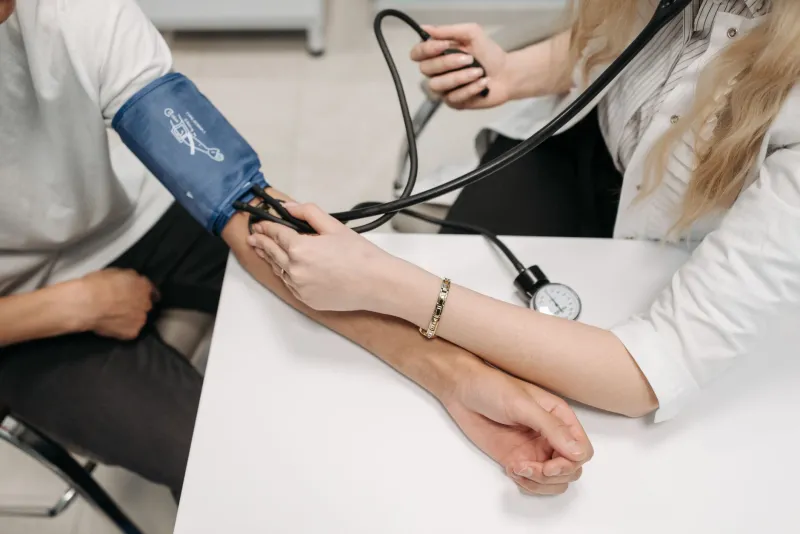
For many patients, the annual physical is a ritual performed on faith. We show up, we answer questions, we let someone wrap a cuff around our arm, and we leave with a vague sense that we have done something responsible for our health. That sense is not wrong — preventive visits genuinely catch problems early — but the visit works better when you understand what is being measured and why.
At our clinic, we believe an informed patient is a partner in care, not a bystander. Consider this your plain-language guide to the exam you may have been getting for decades.
The Numbers That Open Every Visit
Almost every physical begins with vitals, and each one tells a story.
Blood pressure measures the force of blood against your artery walls. A reading near 120/80 mmHg is the general target for most adults; consistently higher numbers suggest hypertension, which raises the risk of heart attack, stroke, and kidney disease. A single elevated reading is not a diagnosis — white-coat effect is real — which is why patterns across visits matter more than any one number.
Heart rate at rest typically falls between 60 and 100 beats per minute. Athletes often run lower, which is usually fine, but an unexplained fast or irregular rhythm deserves follow-up.
Height, weight, and BMI are less about judgment than tracking. A gradual upward trend over several years is a conversation starter about metabolism, thyroid function, or lifestyle factors — not a verdict.
Temperature and oxygen saturation round out the picture and are usually unremarkable, which is itself useful information.
What the Bloodwork Actually Screens For
If your physical includes labs, you are likely being checked for a handful of common conditions:
- A lipid panel measures cholesterol and triglycerides. Your provider is looking at the balance between LDL (the kind that builds up in arteries) and HDL (the kind that helps clear cholesterol away), along with triglycerides, which respond strongly to diet, alcohol, and blood sugar.
- A fasting glucose or A1C screens for prediabetes and diabetes. A1C reflects your average blood sugar over roughly three months, so it captures trends a single glucose reading can miss.
- A complete blood count checks red cells, white cells, and platelets. Low red cells can point to anemia; abnormal white cells can hint at infection or, less commonly, something requiring closer study.
- A metabolic panel reviews kidney and liver function along with electrolytes — the quiet workhorses that medications and dehydration can disturb.
- A thyroid-stimulating hormone (TSH) test may be included, since an underactive or overactive thyroid can mimic fatigue, weight changes, and mood shifts.
Not every patient needs every test every year. Age, family history, medications, and symptoms shape the list. If a test is ordered, it is reasonable — and encouraged — to ask what it screens for and what happens if the result is borderline.
Screenings That Change With Age
Preventive care is not one-size-fits-all; it evolves as you do.
In your 20s and 30s, the emphasis is on blood pressure, cholesterol baselines, cervical cancer screening for women, sexually transmitted infection testing where relevant, and mental health. Skin checks and dental visits belong on the calendar too.
In your 40s, colorectal cancer screening often begins — current US guidance starts at age 45, sometimes earlier with a family history. Many patients choose colonoscopy; stool-based tests are a valid alternative worth discussing.
In your 50s and beyond, mammography, lung cancer screening for long-term smokers, bone density testing for women, and abdominal aortic aneurysm screening for men who have smoked all enter the conversation. Vaccinations shift as well: shingles, pneumonia, and updated boosters become part of the plan.
Your provider tailors this schedule to you. The right question is never "Do I need everything?" but "What do I need, and when?"
The Part Patients Skip: The Conversation
The most valuable portion of a physical is often the last five minutes. This is your window. Useful questions include:
- Which of my numbers changed since last year, and why?
- Am I due for any screenings or vaccines in the next twelve months?
- Do any of my medications interact with each other or with supplements I take?
- What is one thing I could change that would most improve my health?
Bring a written list. Providers genuinely appreciate it, and it keeps the visit focused on what matters to you rather than what simply comes up.
After the Visit
Results rarely arrive during the appointment itself. Ask how and when you will receive them — a patient portal, a phone call, or a follow-up visit — and what to do if a value is flagged. A physical that ends without a follow-up plan is only half finished.
The goal of the annual physical is not to generate paperwork. It is to establish a baseline, catch slow-moving problems while they are still easy to address, and build a relationship with a care team that knows your history. Arrive with questions, leave with answers, and the ritual becomes what it was always meant to be: care, not ceremony.


