Reading Your Own Report Card: A Patient's Guide to Understanding Vitals, Ratios, and Ranges
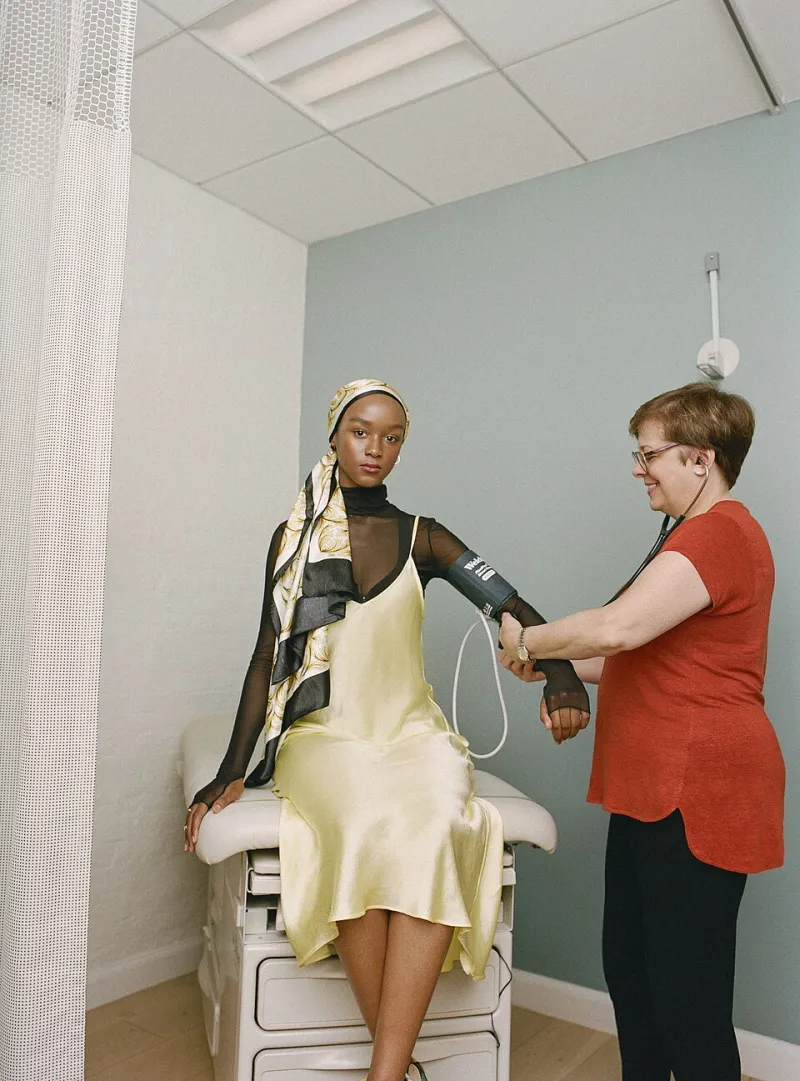
Photo: SELF Magazine, CC BY 2.0, via Wikimedia Commons
Every annual physical in America seems to end the same way: a slip of paper, a portal notification, and a column of figures that most of us scan the way we scan a restaurant bill — quickly, anxiously, and without really knowing what we're looking for.
A number appears. It sits outside the shaded "normal" range on the chart. And then the questions begin. Is this serious? Should I have asked more? Is it nothing?
At our clinic, we would rather patients leave with a conversation than a grade. Here is a grounded look at the three numbers patients ask about most — body mass index, blood pressure, and cholesterol — and why each one tells you less on its own than it does in context.
Body Mass Index: A Screening Tool, Not a Verdict
BMI is calculated from height and weight alone, which makes it fast, free, and — for many people — misleading. It cannot distinguish between muscle and fat, it does not indicate where weight is carried on the body, and it was built from population averages that do not account for differences in age, ancestry, or body composition.
A lifelong athlete with a BMI of 28 may be in better metabolic health than someone with a "normal" BMI and a sedentary lifestyle. An older adult whose BMI drifts downward may face risks that a lower number masks rather than reveals.
What matters more, in most clinical conversations, is the trend over time and the company the number keeps: waist measurement, blood pressure, glucose, and activity level. BMI opens a discussion. It should never close one.
Blood Pressure: The Number That Rewards Repetition
Blood pressure is the rare vital sign you can measure at home, and that matters — because a single reading in a clinic tells you how your body responded to parking, traffic, and a waiting room, not how it behaves on an ordinary Tuesday.
Current US guidelines flag readings at or above 130/80 as elevated, but a diagnosis of hypertension is rarely made on one visit. Providers look for consistency across multiple appointments, and increasingly, they look at home logs.
If your reading was high this year, the useful question is not "Am I sick?" but "What does this look like across a week?" Bring a written log or a cuff's memory function to your next visit. A week of morning readings gives your provider something a single snapshot never can.
Cholesterol Ratios: Why the Total Matters Less Than the Parts
A total cholesterol number is a bit like a single price tag on a bundle of very different goods. The breakdown — LDL, HDL, and triglycerides — carries the meaning, and even then, interpretation depends on the rest of you.
Two patients with identical LDL levels may receive entirely different recommendations because one has diabetes, a family history of early heart disease, or a smoking history, and the other does not. Risk calculators used in American primary care fold in age, blood pressure, and other factors precisely because no lipid number stands alone.
The right question at your visit is not "Is my cholesterol high?" but "Given my overall risk, what would you want this number to be, and why?"
Ranges Are Averages, Not Instructions
Reference ranges on lab reports are drawn from population statistics — typically the interval covering the middle 95 percent of tested, presumably healthy people. By definition, one in twenty healthy people falls outside them.
A mildly low result in an otherwise well patient may warrant a recheck. The same result in a patient with fatigue, weight change, or a relevant family history may warrant a workup. Context is not a footnote to the numbers; it is the numbers' only real meaning.
How to Talk About Results Without Panic — or Dismissal
Both extremes are common. Some patients see one out-of-range value and assume the worst; others shrug off a pattern of borderline readings because "nothing was actually flagged." A middle path exists:
- Ask what changed. Compare this year's values to last year's. Direction often matters more than position.
- Ask what the number is used for. Every value on your report feeds a decision somewhere. Knowing which decisions helps you judge urgency.
- Ask what would change the plan. If a result is being watched rather than treated, ask what threshold would turn watching into action.
- Ask for the follow-up date. A recheck in three months is a plan. "We'll keep an eye on it" is not.
The Point of the Numbers
No single figure from your physical is a grade, a prophecy, or a final word. They are inputs — and like any inputs, they improve the decisions made with them when the person collecting them understands what they represent.
Bring your questions to your next visit. Bring last year's report, a home log if you have one, and the assumption that your provider would rather explain than reassure. The numbers are the beginning of the conversation, not the end of it — and the conversation is where your care actually happens.